
Ageless Precision
Longevity Reimagined.
Fiduciary Standard.

Personalized, physician-led longevity care grounded in advanced diagnostics, microbiome science, and evidence-based protocols—designed to extend healthspan with uncompromising precision. Delivered seamlessly, wherever you are.

Our Mission
Personalized.
Gut Microbiome Expertise.
Amid constant demands to do more, the real question isn’t how much time you have - it’s how you live it.
In a world where few things money can’t buy, time and wellness stand apart. At LongevIQ GI, we unlock the promise of longer, fuller life - through precision diagnostics, gut microbiome mastery and bespoke longevity protocols.

Rewriting the Trajectory of Aging
Most healthcare reacts to disease. Few systems actively manage the trajectory of aging.
Medicine 3.0 reframes health as an asset requiring continuous oversight — identifying risk before symptoms, intervening before damage, and preserving high-level performance across decades. The objective is not simply extending lifespan. It is restructuring how those years are experienced.
What follows is the difference between passive aging and disciplined biological stewardship.
From Lifespan to Healthspan
How Medicine 3.0 Changes Biological Outcomes
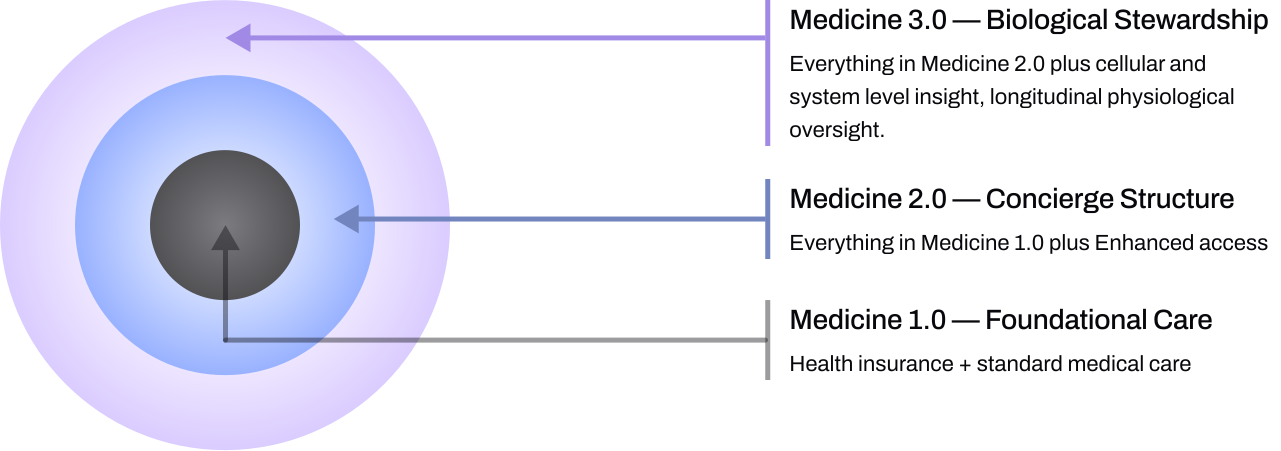
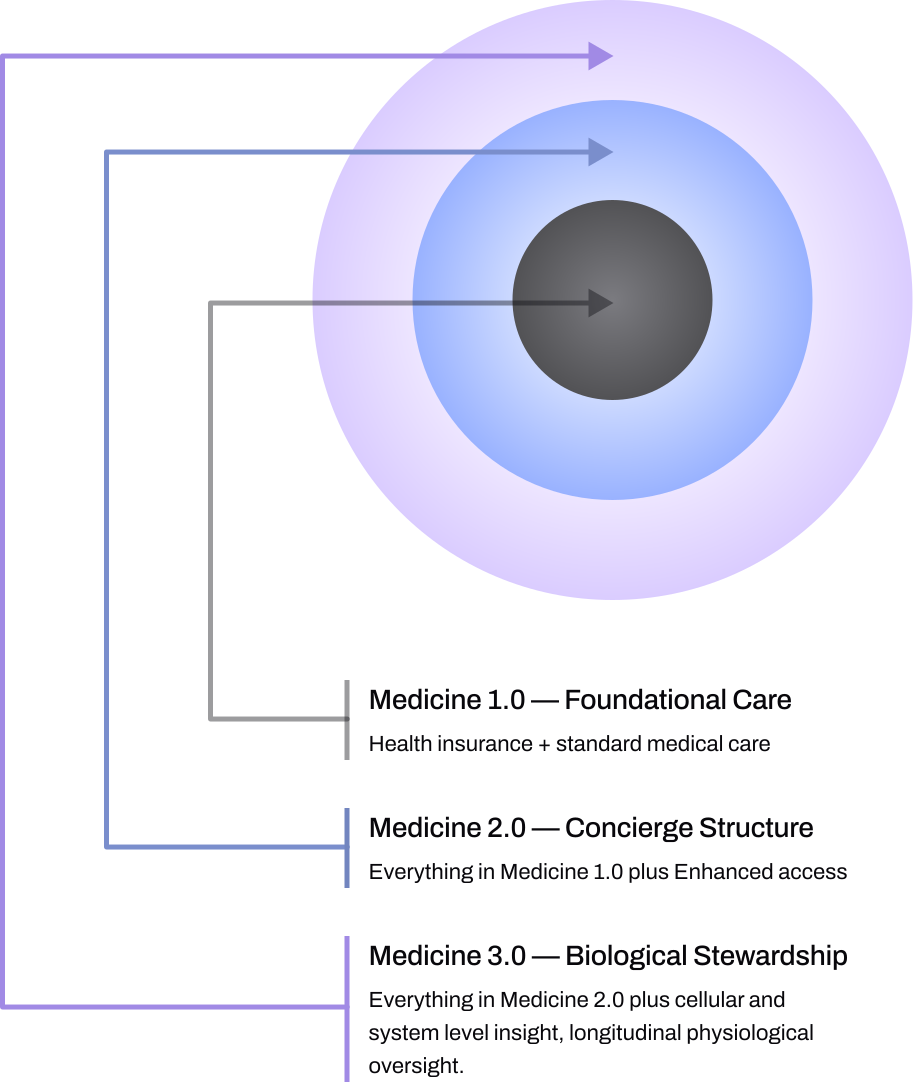
Medicine 1.0 — Extended Lifespan
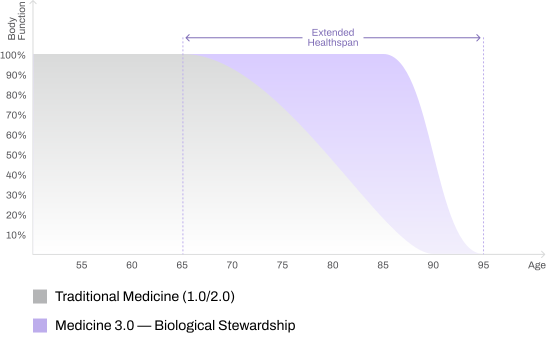
Conventional medicine added decades to life expectancy through antibiotics, surgery, and disease management. But those extra years often came with prolonged decline—longer life, not necessarily better life.
Medicine 2.0 — Improved Quality
Concierge medicine enhanced the experience of care—faster access, better coordination, more convenience. Yet it remained reactive, intervening after disease established.
Medicine 3.0 — Optimizes Biology
Proactive biological stewardship compresses morbidity by identifying and addressing dysfunction before irreversible decline. The result: extended healthspan, not just lifespan—more years lived at full capacity.
The Legacy and Longevity Arc
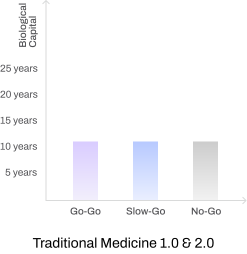
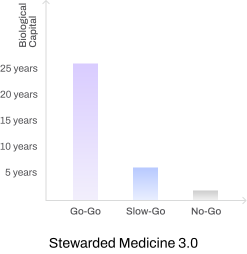
Traditional retirement planning allocates more discretionary capital to the early “Go-Go” decade — when health supports travel, engagement, and autonomy — and gradually prepares for rising healthcare expenditure and long-term care coverage in later years. That model is rational within a system designed to manage disease after it manifests.
LongevIQ GI operates upstream of that model.
Through early detection, precision prevention, and longitudinal accountability, we aim to expand peak-function decades, compress morbidity, and reduce prolonged dependency.
This is not convenience medicine.
It is biological insurance for sustained capability.
Who We Serve
Our clients are high-achieving individuals and discerning families who view health as their most valuable asset. For principals, operators, and multi-generational families who recognize that biological resilience is not an afterthought—it is the enabling infrastructure for sustained performance across decades, not quarters.Whether you’re managing a demanding career, planning for generational longevity, or recovering from burnout — we provide the structure, science, and strategic care to support your goals. We provide the flexibility to coordinate directly with your assistant, secretary or family office manager for a seamless, whiteglove experience.
Elite, science-backed care designed for high-performing individuals and families — led by a board-certified gastroenterologist. We combine advanced diagnostics, gut microbiome insights, and proactive longevity strategies to help you live longer, feel stronger, and shape your aging on your own terms.
We combine advanced biomarker profiling with the forefront of longevity science to curate and deliver a personalized, data-driven plan ----designed to enhance vitality, extend health span, and support a life of exceptional quality and longevity.
What unites every client we serve is a single conviction : biological capital deserves the same rigorous stewardship as financial capital.
That is what a Health Fiduciary does.

Executives & Entrepreneurs

Health-Conscious Families who understand the power of legacy

Performance-Driven Professionals

High achieving individuals, discerning families and preventive thinkers
The LongevIQ Journey
Gut Microbiome Expertise.
At LongevIQ GI, we combine the most advanced diagnostic technologies, and deep microbiome expertise to not merely adding years to your life but enriching the years you have.
In our fast-paced modern world, that constantly pushes for more, we believe true fulfillment lies not just in the quantity of time, but in the quality of how it's lived.
Step into a new era of longevity medicine: a tailored, personalized approach crafted to activate your peak performance and realize the finest version of yourself. We purposefully walked away from one size fits all and surface level wellness, that is offered in many clinics, and aim to deliver science backed approach to prevent, slow or reverse aging, and cultivate vitality, fuel your wellness, and unlock a more dynamic you.
Discovery & Baseline
We begin with an indepth virtual consultation, where you share your goals, health history, lifestyle and aspirations. Then we deploy the most advanced diagnostics — gut microbiome profiling, advanced biomarker panels, Whole body imaging, Epigenetic testing (testing may vary depending on your membership level) — to establish your unique baseline.
Strategic Plan Development
Using the data we’ve gathered, we craft a scientifically rooted, personalized plan. This plan integrates gut microbiome optimization, longevity science, lifestyle, personalized nutrition planning and optional nutraceuticals/supplements — designed not just to add years to your life, but to enrich them.
Implementation & Activation
With your plan in place, we support you through implementation: guided interventions, gut microbiome therapies, and strategic lifestyle shifts — all coordinated to raise vitality, extend healthspan, and empower your best self.
Ongoing Optimization & Longevity Stewardship
Your journey doesn’t stop at implementation. We continuously monitor, refine, and evolve your plan: retesting key biomarkers, adjusting protocols, and staying ahead of aging dynamics — so your health remains vibrant and forward-looking.
Why Early Detection Changes Everything
Breakthrough diagnostics uncover risks years before symptoms appear — giving you the advantage of time.
is the accuracy with which gut microbiome can distinguish healthy to diseased individual[1]
of cancers detected on preventive whole-body MRI have no recommended screening pathway[2]

increase in cancer detection when MCED (multi cancer early-detection) blood test is combined with recommended standard screening[3]
What Makes Us Different
Redefining Longevity Through Gut Intelligence
Emerging research increasingly underscores the critical role of the gut microbiome in our overall health, highlighting its profound effect on nearly every aspect of life and its substantial influence on both healthspan and lifespan. Led by a board-certified gastroenterologist, we view gut health as the gateway to lifelong vitality.
Experience elite care on your schedule — including evening and weekend availability. We ensure your health fits seamlessly into your lifestyle, without disrupting your personal or professional commitments.
Receive world-class concierge care from the comfort of your home or wherever you may be — from your primary residence to your summer beach estate. We coordinate virtual consultations and all supporting logistics so your health never interrupts your life.
Our difference lies in our simplicity and depth. In a world full of quick fixes and fleeting trends, we offer something different: a return to what truly matters. Our methodology is grounded in rigorous, evidence-based lifestyle interventions proven to enhance healthspan. We intentionally avoid unvalidated trends, focusing instead on interventions supported by science, data, and long-term outcomes.
We serve discerning clients who value confidentiality, autonomy, and seamless virtual care.
We don’t guess — we test. Every decision is backed by objective biomarkers and imaging.
We partner only with the highest tier, CLIA-certified laboratories and best in class imaging centers where advanced whole body MRI scans are read only by board-certified radiologists, ensuring the gold standard of precision and reliability.
We don’t just hand you data; we interpret it and provide a clear, actionable roadmap toward optimized health.
High-touch care virtually accessible from anywhere, without sacrificing quality or connection.
We identify and address problems before symptoms arise — extending both healthspan and peace of mind.
Read about Longevity
Curated articles featuring longevity science, gut health breakthroughs, diagnostics, and performance insights.

The Greatest Unmanaged Risk in the Portfolio
Executive Summary
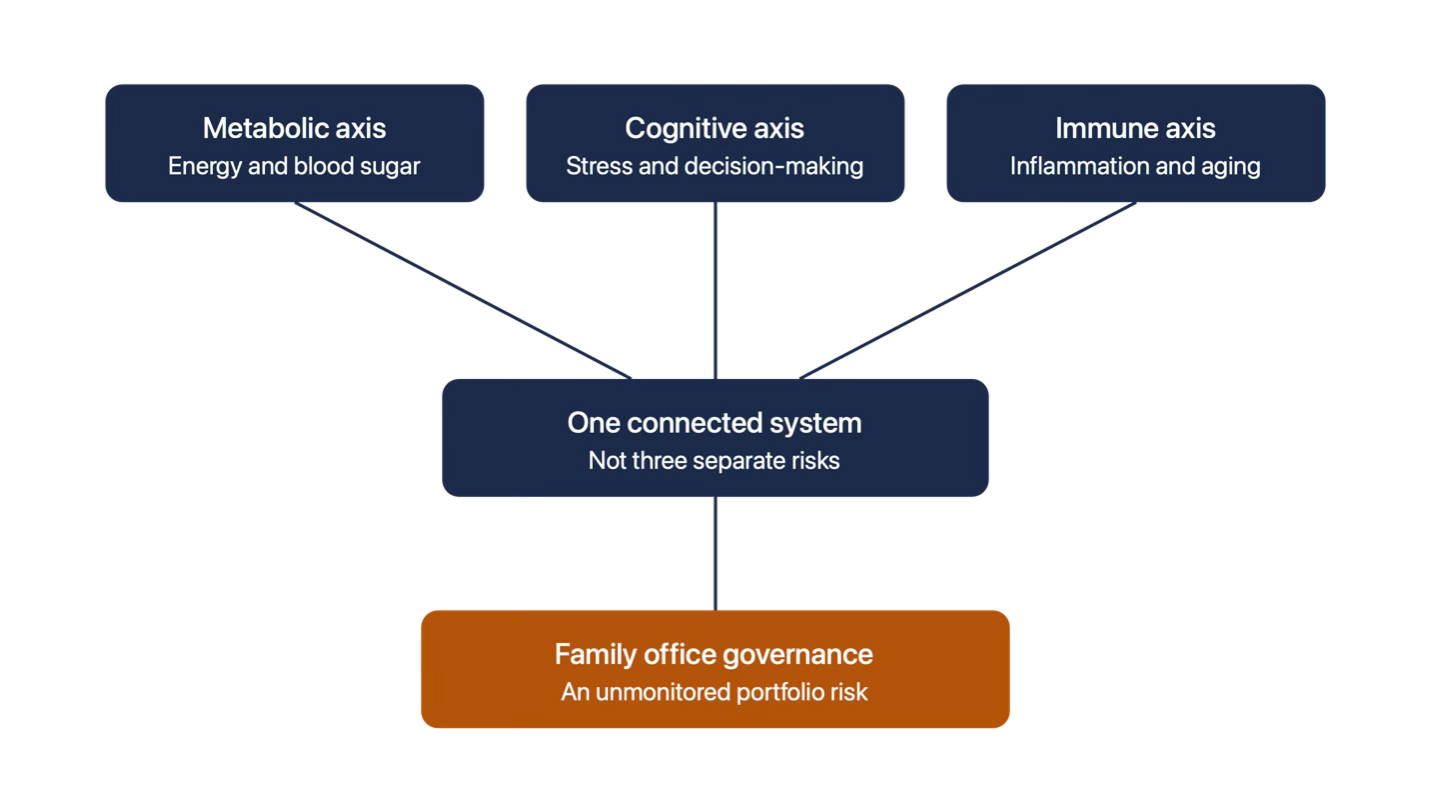
Family offices maintain contingency architecture for market shocks, tax changes, and litigation exposure — but not for the health of the principal the entire structure is built around. This is not a wellness gap. It is a governance gap. Chronic, low-grade inflammation is now understood as a central driver of disease and functional decline across the lifespan, and a meaningful share of that burden originates in gut function — a system that shapes metabolic efficiency, immune regulation, and the neuroendocrine stress response together, not separately. This paper makes the case across three physiological domains: metabolic, cognitive, and immune. Central to the cognitive case is a distinction worth naming plainly — physical lifespan and cognitive lifespan are not the same thing, and it is the latter, not longevity alone, that governs sound decision-making during the narrow windows when succession and governance actually happen. Treated together, these three domains describe one interconnected system, not three unrelated arguments — which is precisely what makes it a systemic risk factor rather than a minor one. The conclusion is not a diagnosis or a protocol. It is a case for visibility: biological risk sits, unhedged and unmonitored, inside every wealth and estate plan built around a principal.
Introduction — The Unhedged Position
Family offices maintain contingency architecture for almost every category of risk that could disrupt a family's wealth: market shocks, tax law changes, litigation exposure, succession disputes. One category remains almost entirely unaddressed — the health of the individual the entire structure is built around.
This is not a wellness gap. It is a governance gap. The single event most likely to convert an orderly, well-planned transition into an abrupt, poorly managed one is not a market downturn or a competitor's move — it is a sudden decline in the health of the principal, occurring without warning because no formal framework exists to monitor for it.
Chronic, low-grade inflammation is now understood to be a central driver of disease and functional decline across the lifespan — a finding established firmly enough in the medical literature that it anchors current thinking in gero-science broadly. ¹ Much of that inflammatory burden originates in a place, family offices and most physicians, rarely examine closely: the gut. The gastrointestinal tract does more than digest food. It regulates a family of biological processes — metabolic efficiency, immune calibration, and the neuroendocrine stress response — that together shape how a person ages, how their cognitive capacity holds up under sustained pressure, and how resilient they are to the kind of health shock that disrupts continuity planning.
This is also, notably, an area longevity medicine as a category has been slow to take seriously. The most visible players in executive health and longevity diagnostics build their offerings around imaging and biomarker panels, generally overseen by physicians without specific gastroenterological training.
What follows is a three-part case for why gut-microbiome function belongs inside the family office's risk architecture: its role in metabolic health, in cognitive and stress resilience, and in immune regulation and biological aging. Each pillar is treated on its own evidentiary terms — where the science is well-established, that is stated plainly; where it remains early or associative, that is stated just as plainly. The goal is not to sell a diagnosis. It is to make the case that this is a real, measurable, and currently unmonitored variable in the portfolio.
The larger point is structural, not clinical. Biological risk sits, unhedged and unmonitored, inside every wealth and estate plan built around a principal — the one category the advisory platform has no visibility into. This paper makes the case, across three physiological domains, for why that should change.
Pillar I — Metabolic
Every cell in the body runs on energy, and the raw material for that process is shaped upstream by gut bacteria in ways only recently understood. When gut microbes ferment dietary fiber, they produce short-chain fatty acids — acetate, propionate, and butyrate — that function less like waste products and more like chemical messengers, signaling to the liver, fat tissue, and muscle how to handle glucose and fat. ²
Butyrate is the most consequential of the three. It activates a cellular switch called PGC-1α that triggers cells to build more mitochondria — the structures that generate energy — directly improving how efficiently the body burns fat and processes fuel. ³ The same molecule also acts on gene expression itself, functioning as a kind of epigenetic dial that influences which metabolic programs a cell turns on or off. ⁴
The clinical stakes are concrete. In a randomized controlled trial, a butyrate-based intervention measurably improved fasting glucose, long-term blood sugar control, and insulin resistance in patients with type 2 diabetes — real interventional evidence, not just an association.⁵ Related mechanisms extend to fat tissue itself: these same signaling molecules help the body store and mobilize fat appropriately, and when that signaling breaks down, fat is deposited in places it shouldn't be, a pattern strongly linked to insulin resistance and metabolic disease.⁶
The evidence is not uniform in every direction, and that is worth stating plainly. At least one well-designed human study found that circulating levels of one of these molecules, acetate, moved in the opposite direction from what animal research would predict — a reminder that this system is genuinely complex, and human physiology does not always mirror laboratory models cleanly. ⁷
What this means in practical terms: the capacity to produce these compounds is not fixed. It depends on the diversity of the microbial population doing the producing, which in turn depends on diet, and depletes quietly, well before it shows up on a standard lab panel. ⁸
Pillar II — Cognitive / Neuroendocrine
Sustained stress does not stay contained to the mind. The body's stress-response system — the HPA axis, which governs cortisol release — and the gut are in constant two-way communication, and chronic activation of one measurably degrades the other. Elevated cortisol changes the gut's permeability, allowing bacterial byproducts to enter circulation and trigger low-grade inflammation that, over time, feeds back and keeps the stress response elevated — a self-reinforcing loop rather than a one-time event. ⁹
The clearest evidence for how severe this can become comes from patients with Cushing's syndrome, a condition of extreme, sustained cortisol excess. These patients show measurable gut-barrier breakdown and a shift in bacterial populations, including one species that actively metabolizes cortisol itself.¹⁰ A separate genetic study found a causal relationship — not just an association — between specific gut bacteria and adrenal hormone output.¹¹ It is worth being precise about what this evidence does and does not show: these findings establish that the cortisol-gut relationship is real and mechanistically serious, but they were observed at a pathological extreme of hormone exposure, not every day occupational stress. Extending them directly to a demanding but ordinary work life is a reasonable hypothesis, not a settled finding.
The second communication channel runs through the vagus nerve, the body's primary gut-to-brain wire. It continuously reads chemical signals produced by gut bacteria and relays them to the brain, while a parallel signal travels the other way, helping keep inflammation in check. ¹² In one randomized controlled trial, patients given a specific probiotic showed measurably improved vagal nerve function after three months compared to a control group — a real intervention with a real physiological result, not simply an observed pattern.¹³
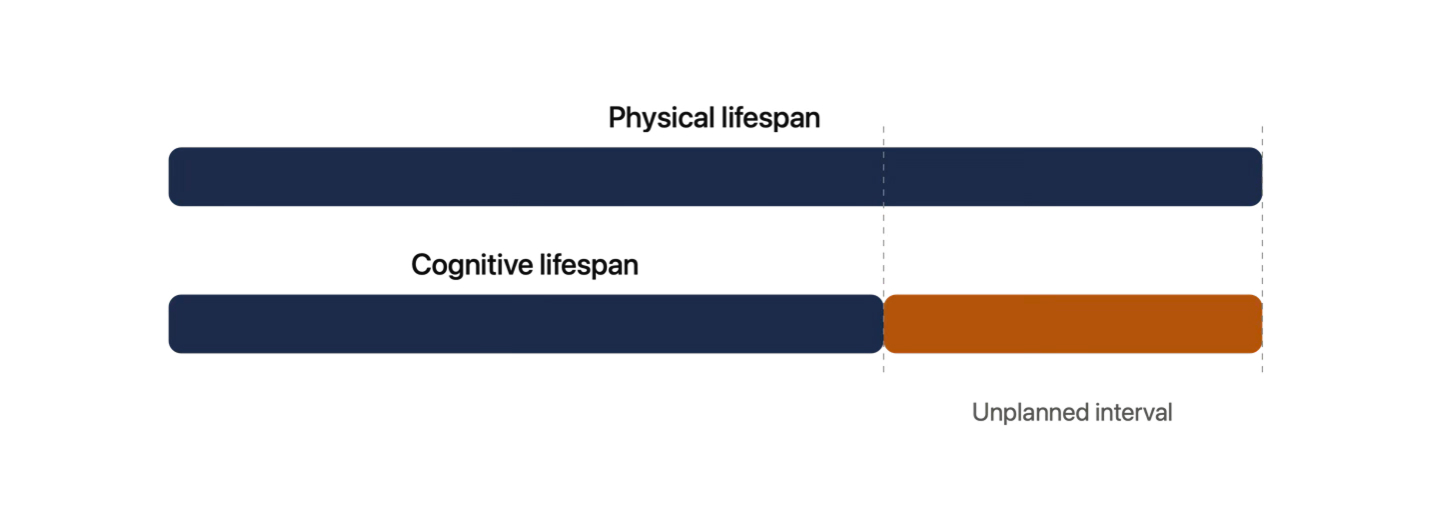
Together, these two systems point toward a distinction worth naming explicitly: physical lifespan and what might be called cognitive lifespan are not the same thing. The capacity to continue making sound, high-stakes decisions under sustained pressure is itself a biological variable — one shaped by exactly the stress-gut mechanisms described above — and it is this capacity, not lifespan alone, that matters most during the narrow windows when succession and governance decisions actually get made.
Pillar III — Immune / Inflammatory
The gut is also the body's largest immune organ, and a meaningful share of the immune system's daily calibration happens there. Specific gut bacteria train a class of immune cells called regulatory T cells to keep inflammation in check — teaching the immune system, in effect, what to tolerate and what to attack. ¹⁴ The same short-chain fatty acids central to the metabolic pillar do much of this work, meaning metabolic health and immune regulation are not separate systems so much as two expressions of the same underlying biology.¹⁵
This regulatory capacity erodes with age. Older adults show reduced microbial diversity and a corresponding decline in immune tolerance, creating a self-reinforcing cycle: less diverse bacteria weaken immune regulation, weakened immune regulation further destabilizes the microbiome, and the result is a state of chronic, low-grade systemic inflammation now referred to in the research literature as "inflammaging."¹⁶
Not everyone follows this trajectory equally. Research on centenarians — people who reach exceptional age in good health — consistently finds they retain a distinctive, favorable set of gut bacteria associated with preserved immune regulation, even into their tenth and eleventh decades. ¹⁷ This is among the more direct pieces of evidence connecting gut-microbial health specifically to longevity, rather than to any single downstream marker of it.
The immune and stress-response systems described in the preceding pillars do not operate independently. When the gut barrier weakens — through the cortisol-driven mechanism described earlier, through age, or through diet — bacterial components enter circulation and trigger the same inflammatory cascade at the center of this pillar, which in turn keeps the stress-response system activated. ¹⁸ The three pillars of this paper are, in this sense, one interconnected system observed from three different angles, not three unrelated arguments.
Convergence — Why Three Axes, One System
Treated separately, the metabolic, cognitive, and immune pillars each make a bounded, modest case. Treated together, they describe a single regulatory system with three points of entry.
The same signaling molecules that govern metabolic efficiency in Pillar I are the ones training immune tolerance in Pillar III. The same barrier-integrity mechanism disrupted by chronic stress in Pillar II is the mechanism that, when it fails, drives the inflammatory cascade at the center of Pillar III. None of these are three separate stories that happen to share a source organ. They are three views of one system, and the research increasingly treats them that way — chronic, low-grade inflammation is now understood as a central mechanism linking disease and functional decline across virtually every organ system, not a downstream symptom confined to any one of them. ¹
This convergence is where the longevity claim becomes most concrete. Bacterial populations associated with preserved immune function are consistently overrepresented in people who reach exceptional age in good health, which is about as direct a link between gut-microbial composition and long-term outcome as the current evidence provides.¹⁷ A separate line of research finds that microbial diversity tracks with measurably better cognitive standing in midlife populations — a weaker, cross-sectional finding that cannot establish cause and effect, but one that is consistent with, rather than contradicting, the mechanistic case built across the three pillars above.¹⁹
None of this argues that gut health is the sole determinant of healthy aging. It argues that it is a legitimate, measurable, and currently unmonitored input into it — one operating through three converging channels rather than one narrow pathway, which is precisely what makes it a systemic risk factor rather than a minor one.
Implication for Family Office Governance
None of the above is presented as a case for any particular treatment, product, or protocol. It is presented as a case for visibility — the same case a family office would make for adding any other category of unmonitored risk to its governance framework.
The distinction between physical lifespan and cognitive lifespan, introduced earlier, is where this becomes operationally relevant. A family office's contingency planning typically assumes a principal will either be present and capable, or absent. The scenario least planned for — and arguably most common — is a principal who is physically present, but whose decision-making capacity has quietly degraded under years of sustained, unaddressed physiological load. That is not a hypothetical edge case. It is the direct, biologically plausible consequence of the mechanisms described across the three pillars above.
This suggests a modest, concrete addition to existing governance practice: treating a principal's underlying physiological resilience as a data point worth having on file, in the same spirit that a family office already tracks key-person insurance, succession timelines, and estate liquidity — not as a diagnosis, and not as a substitute for medical judgment, but as one more input into a continuity framework that currently has none.
The alternative is the status quo: a governance structure that plans meticulously for every category of risk except the one most likely to determine whether any of the others is ever triggered in an orderly way.
This governance checklist — ten questions for assessing whether key-person health risk is currently tracked in a family office's continuity planning — is available as a complete reference document for RIAs, multi-family offices, and the principals they advise.
Dr. Banerjee is a board-certified gastroenterologist with over 16 years of clinical experience, peer-reviewed publications indexed in PubMed, and deep expertise in gut microbiome science. He advises high-achieving individuals and families on precision longevity and healthspan optimization across Pennsylvania and Florida.
Endnotes
- Furman D, Campisi J, Verdin E, et al. Chronic inflammation in the etiology of disease across the life span. Nat Med. 2019;25(12):1822-1832. (cited twice: Introduction and Convergence)
- Sasidharan Pillai S, Gagnon CA, Foster C, Ashraf AP. Exploring the Gut Microbiota: Key Insights Into Its Role in Obesity, Metabolic Syndrome, and Type 2 Diabetes. J Clin Endocrinol Metab. 2024;109(11):2709-2719; Aron-Wisnewsky J, Warmbrunn MV, Nieuwdorp M, Clément K. Metabolism and Metabolic Disorders and the Microbiome. Gastroenterology. 2021;160(2):573-599.
- Imdad S, Lim W, Kim JH, Kang C. Intertwined relationship of mitochondrial metabolism, gut microbiome, and exercise potential. Int J Mol Sci. 2022;23(5):2679.
- Mann ER, Lam YK, Uhlig HH. Short-chain fatty acids: linking diet, the microbiome and immunity. Nat Rev Immunol. 2024;24(8):577-595.
- Panufnik P, Więcek M, Szwarc P, et al. Effect of microencapsulated sodium butyrate on abdominal symptoms and carbohydrate metabolism in patients with type 2 diabetes: a randomized placebo-controlled trial. Sci Rep. 2026;16(1):17404.
- Cani PD, Van Hul M. Gut microbiota in overweight and obesity: crosstalk with adipose tissue. Nat Rev Gastroenterol Hepatol. 2024;21(3):164-183; Canfora EE, Jocken JW, Blaak EE. Short-chain fatty acids in control of body weight and insulin sensitivity. Nat Rev Endocrinol. 2015;11(10):577-91.
- Müller M, Hernández MAG, Goossens GH, et al. Circulating but not faecal short-chain fatty acids are related to insulin sensitivity, lipolysis and GLP-1 concentrations in humans. Sci Rep. 2019;9(1):12515.
- van Deuren T, Blaak EE, Canfora EE. Butyrate to Combat Obesity and Obesity-Associated Metabolic Disorders: Current Status and Future Implications for Therapeutic Use. Obes Rev. 2022;23(10):e13498.
- Zhang H, Wang Z, Wang G, et al. Understanding the Connection Between Gut Homeostasis and Psychological Stress. J Nutr. 2023;153(4):924-939; Tena-Garitaonaindia M, Arredondo-Amador M, Mascaraque C, et al. Modulation of Intestinal Barrier Function by Glucocorticoids: Lessons From Preclinical Models. Pharmacol Res. 2022;177:106056.
- Zhang M, Shi Z, Wu C, et al. Cushing Syndrome Is Associated With Gut Microbial Dysbiosis and Cortisol-Degrading Bacteria. J Clin Endocrinol Metab. 2024;109(6):1474-1484.
- Liu T, Ji H, Li Z, et al. Gut microbiota causally impacts adrenal function: a two-sample mendelian randomization study. Sci Rep. 2024;14(1):23338.
- Bonaz B, Bazin T, Pellissier S. The Vagus Nerve at the Interface of the Microbiota-Gut-Brain Axis. Front Neurosci. 2018;12:49; Cryan JF, O'Riordan KJ, Cowan CSM, et al. The Microbiota-Gut-Brain Axis. Physiol Rev. 2019;99(4):1877-2013.
- Mörkl S, Narrath M, Schlotmann D, et al. Multi-Species Probiotic Supplement Enhances Vagal Nerve Function - Results of a Randomized Controlled Trial in Patients With Depression and Healthy Controls. Gut Microbes. 2025.
- Tanoue T, Atarashi K, Honda K. Development and maintenance of intestinal regulatory T cells. Nat Rev Immunol. 2016;16(5):295-309; Ramanan D, Pratama A, Zhu Y, et al. Regulatory T cells in the face of the intestinal microbiota. Nat Rev Immunol. 2023;23(11):749-762.
- Tan JK, Macia L, Mackay CR. Dietary Fiber and SCFAs in the Regulation of Mucosal Immunity. J Allergy Clin Immunol. 2023;151(2):361-370.
- Nguyen TQT, Cho KA. Targeting immunosenescence and inflammaging: advancing longevity research. Exp Mol Med. 2025;57(9):1881-1892; Wrona MV, Ghosh R, Coll K, Chun C, Yousefzadeh MJ. The 3 I's of immunity and aging: immunosenescence, inflammaging, and immune resilience. Front Aging. 2024;5:1490302.
- Ticinesi A, Maggi S, Nouvenne A, Zuliani G, Franceschi C. The gut microbiome and ageing trajectories: mechanisms and clinical implications. Nat Rev Endocrinol. 2026;22(6):323-337. (cited twice: Pillar III and Convergence)
- Zhang YF, Li YY, Jin J. Chronic Stress at the Crossroads: Decoding the HPA-SAM-immune-gut Axis in Inflammatory Bowel Disease Pathogenesis and Therapeutics. Semin Immunol. 2026;83:102038; Mohammad S, Thiemermann C. Role of Metabolic Endotoxemia in Systemic Inflammation and Potential Interventions. Front Immunol. 2020;11:594150.
- Meyer K, Lulla A, Debroy K, et al. Association of the Gut Microbiota With Cognitive Function in Midlife. JAMA Netw Open. 2022.

The Biological Cost of the Three-Home Life: Microbiome Stability for the Philadelphia–Naples–Palm Beach Circuit
The most expensive part of your flight isn’t the fuel or the crew—it’s the initial 48-hour perturbation window your microbiome requires to begin stabilizing, the first phase of a recovery arc that, without intervention, runs 2–4 weeks. If you are flying 100+ hours a year across this circuit, you are operating at a permanent biological discount.
For the executive or family principal who splits the calendar between Philadelphia, Naples, and Palm Beach, that transition happens multiple times a year—sometimes monthly. The jet bridge, the climate shift, the change in diet and sleep schedule, the stress of compressed itineraries: each represents a perturbation event your gut ecosystem must absorb and recover from. When the frequency of those events outpaces the microbiome’s recovery window, the cumulative deficit shows up not as GI symptoms, but as accelerated inflammatory tone, metabolic drift, and cognitive friction that most high-performers quietly attribute to age or stress.
This is not a wellness concern. It is a biological capital concern. Understanding the mechanisms—and the specific variables the Philadelphia–Naples–Palm Beach circuit introduces—allows for targeted mitigation rather than generic advice about eating well and staying hydrated.
What Air Travel Actually Does to Your Gut
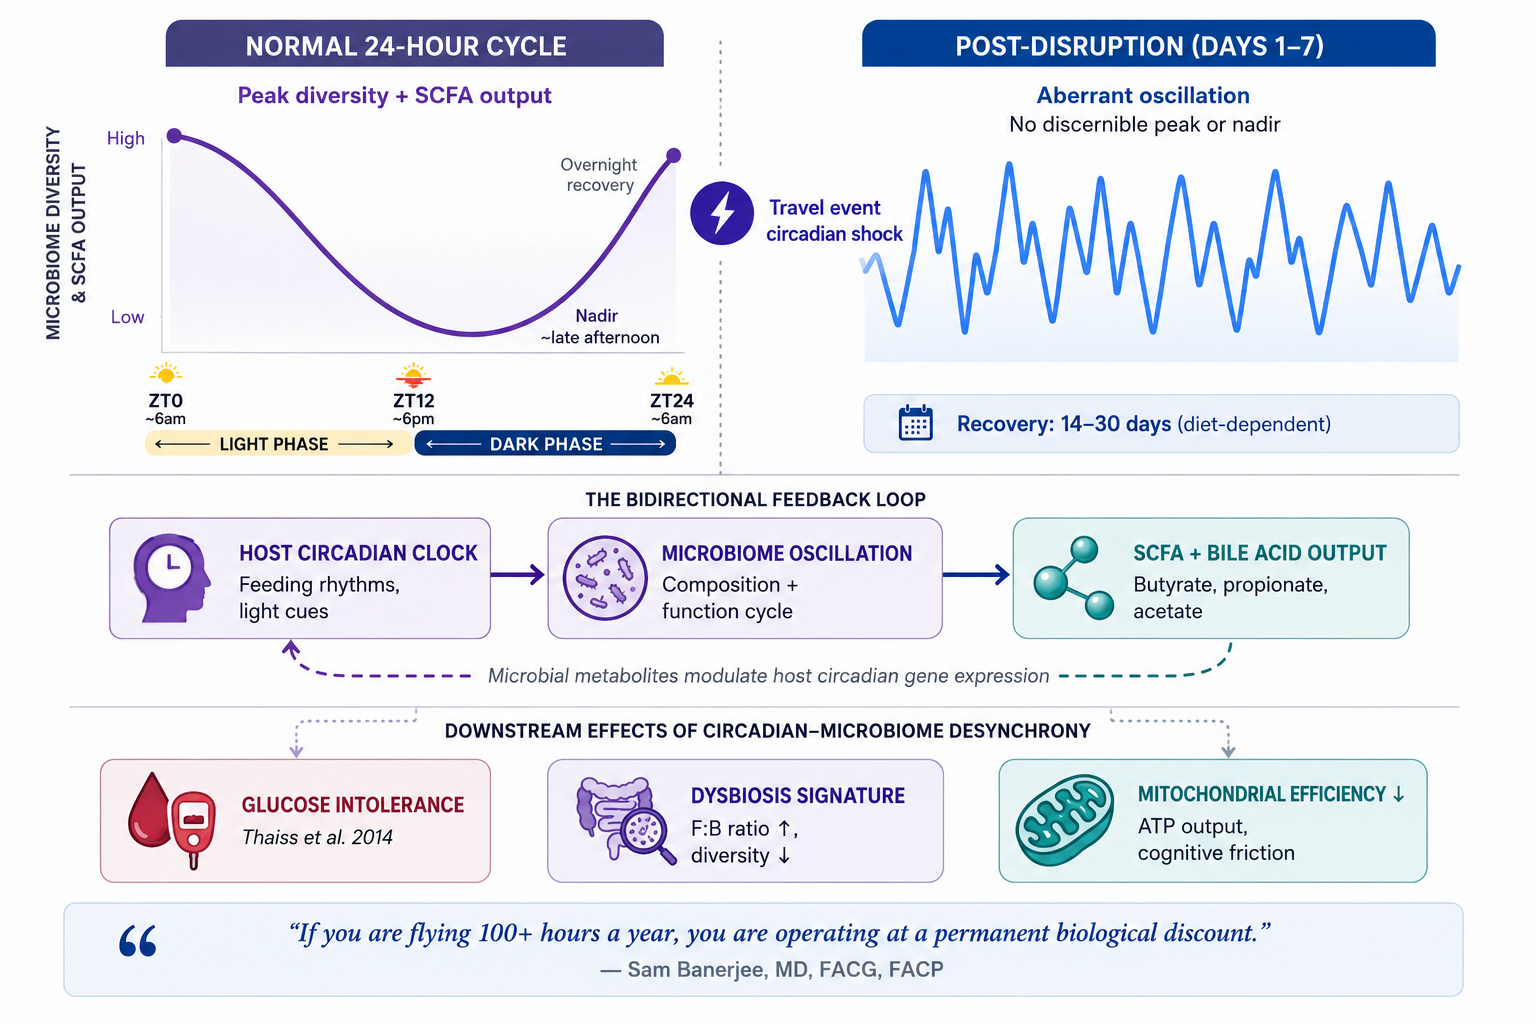
The popular narrative frames inflight microbiome disruption around cabin pressure and recycled air. The evidence points elsewhere. The three operative mechanisms are circadian disruption, dietary and environmental change, and—for frequent international travelers—acquisition of antimicrobial-resistant organisms. The Philadelphia–Naples–Palm Beach route is domestic, which limits the third risk, but the first two operate on every flight regardless of distance.
The circadian-microbiome feedback loop
Thaiss et al. demonstrated in a landmark 2014 paper that jet lag induces aberrant diurnal oscillations in gut microbiota composition—disruptions sufficient to promote glucose intolerance and obesity, with effects transferable to germ-free mice via fecal transplant. This is not a minor finding. It established that host circadian rhythm and microbiome composition are bidirectionally coupled: the microbiome oscillates in composition and function according to feeding rhythms, and when those rhythms are disrupted—as occurs with transmeridian travel—the ecosystem destabilizes.
Chronic circadian misalignment in murine models decreases microbial abundance, richness, and diversity; increases the Firmicutes-to-Bacteroidetes ratio (a recognized dysbiosis marker); and alters tryptophan and secondary bile acid metabolism. A 2025 systematic review confirmed these directional findings in humans, though diversity metrics remain variable across studies. The bidirectionality matters: microbial metabolites including short-chain fatty acids and bile acids modulate host circadian gene expression. Disrupt the host clock, and the microbiome destabilizes. Destabilize the microbiome, and the host clock’s resilience weakens. The feedback loop can self-perpetuate.
Dietary environment as a second perturbation axis
International travel literature provides the most granular data here. A metagenomic analysis of 267 US travelers found significant depletion of microbial diversity and enrichment of Enterobacteriaceae after travel, with 67% of subjects acquiring phylogenetically distinct new E. coli strains. Antibiotic resistance gene burden increased by a median of 15%. The Philadelphia–Naples–Palm Beach circuit does not expose the traveler to the pathogenic microbe profile of developing regions, but the dietary discontinuity—restaurant frequency, alcohol, altered meal timing, reduced prebiotic fiber intake—operates through identical mechanisms at a lower magnitude.
What Makes This Circuit Clinically Distinct
The Philadelphia–Naples–Palm Beach transition is not a single disruption event. For someone making this transition four to eight times annually across both Southwest Florida and the Palm Beach corridor, it is a recurring oscillation that the microbiome must absorb repeatedly, often without full recovery between cycles. Several variables compound the generic travel disruption:
Climate and dietary environment
Philadelphia and the Southwest Florida and Palm Beach corridor represent meaningfully different food environments. The Mediterranean-influenced dietary patterns more accessible in Philadelphia—high-quality olive oil, diverse vegetables, legume-forward eating—shift toward the restaurant-heavy, higher-alcohol, lower-fiber consumption patterns typical of seasonal life in Naples or Palm Beach. Every reduction in prebiotic fiber intake directly reduces SCFA production—particularly butyrate—which is the primary fuel for colonocytes and the upstream regulator of intestinal barrier integrity and systemic inflammatory tone.
Sleep architecture and schedule compression
The Philadelphia–Naples–Palm Beach transition is typically embedded in a compressed itinerary—departures timed around board meetings, closings, or social calendars. Sleep architecture disruption, even without transmeridian jet lag, is sufficient to shift the Firmicutes-to-Bacteroidetes ratio. A single night of poor sleep alters microbiome composition in ways measurable by morning. Over four to six transition events per year across both Florida markets, the cumulative effect on microbial diversity is not trivial.
The recovery window problem
A longitudinal study of travelers to the Caribbean found that gut microbial composition gradually shifted toward local enterotypes during extended stays, then reverted to original profiles within one month of returning home—mediated primarily by dietary normalization. The microbiome is resilient. But one month of recovery assumes the traveler stays home for a month. For the executive rotating quarterly across Philadelphia, Naples, and Palm Beach, the recovery window closes before the next transition opens.
The Gut–Mitochondria Axis: Why This Is an Executive Health Optimization Problem
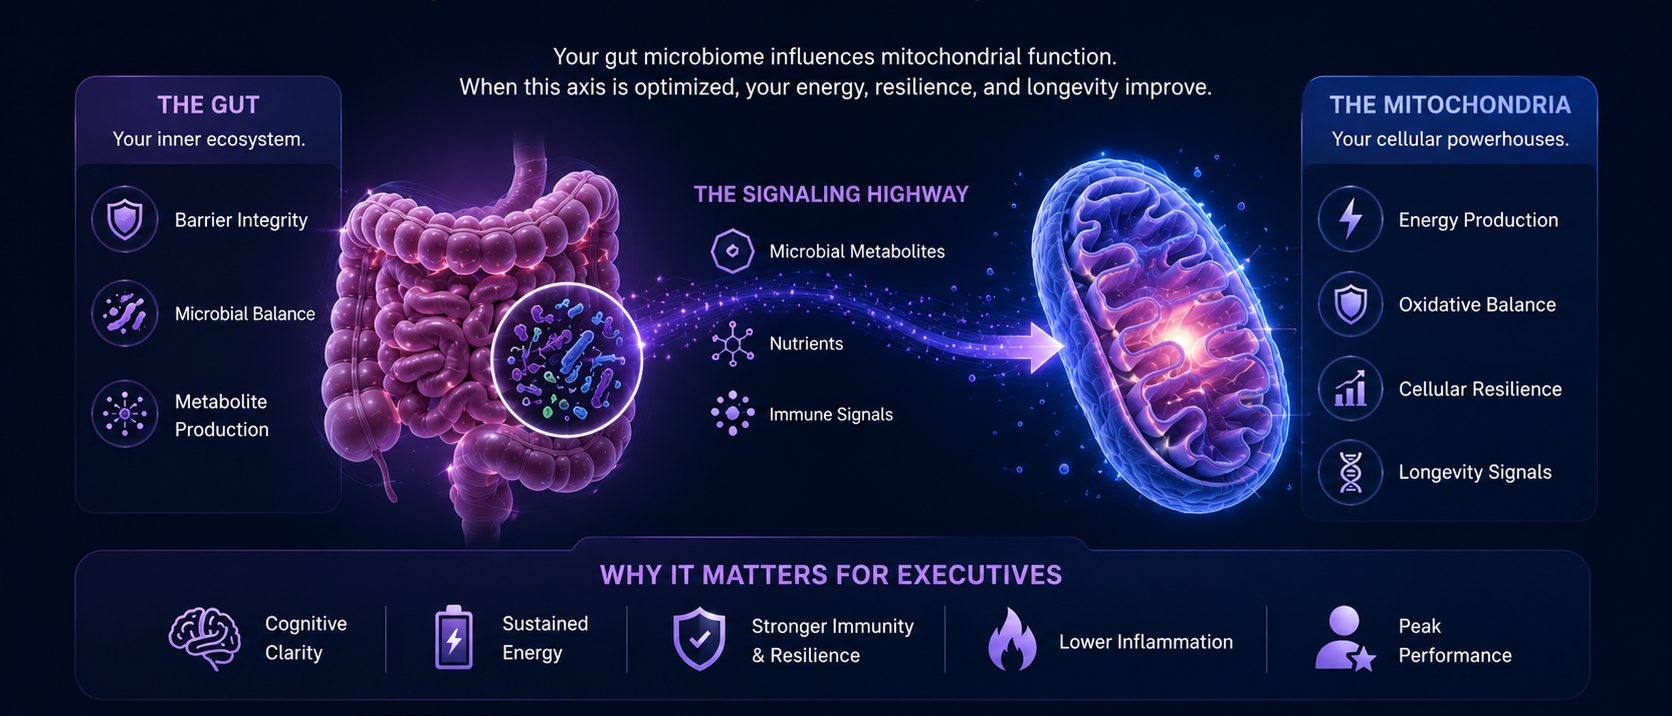
Most travel health frameworks stop at the gut. The clinical picture extends further. The gut microbiome and mitochondrial function are bidirectionally coupled through a set of mechanisms that make travel-induced dysbiosis directly relevant to cognitive performance and metabolic output—not just digestive comfort.
Butyrate—the primary short-chain fatty acid produced by beneficial gut bacteria fermenting prebiotic fiber—stimulates mitochondrial biogenesis through PGC-1α activation and enhances oxidative phosphorylation efficiency. When butyrate-producing taxa are depleted by travel-associated dietary disruption and circadian desynchrony, the downstream consequence is measurably reduced mitochondrial ATP output. This is not a theoretical pathway. It is the mechanism by which gut dysbiosis translates into the cognitive friction and physical fatigue that frequent travelers normalize as the cost of doing business.
The second mechanism is barrier-mediated inflammation. Gut barrier failure—accelerated by the dietary shifts and circadian disruption of repeated travel—allows bacterial lipopolysaccharide to enter systemic circulation. The resulting inflammatory cytokine load directly reduces mitochondrial ATP efficiency and shifts cellular metabolism toward less efficient glycolytic pathways. Mitochondrial supplements including CoQ10 and NAD+ precursors demonstrate measurably reduced efficacy when gut dysbiosis persists—a finding with direct implications for the significant supplement expenditure common among health-conscious executives. You cannot optimize the downstream system while the upstream regulator remains compromised.
For the executive running consequential decisions across three markets, a reduction in mitochondrial ATP efficiency is not an abstraction. It is the biological substrate of slower processing speed, reduced working memory capacity, and diminished stress tolerance. The Philadelphia–Naples–Palm Beach circuit, unmanaged, creates exactly those conditions on a recurring basis.
What Resilient Microbiomes Do Differently
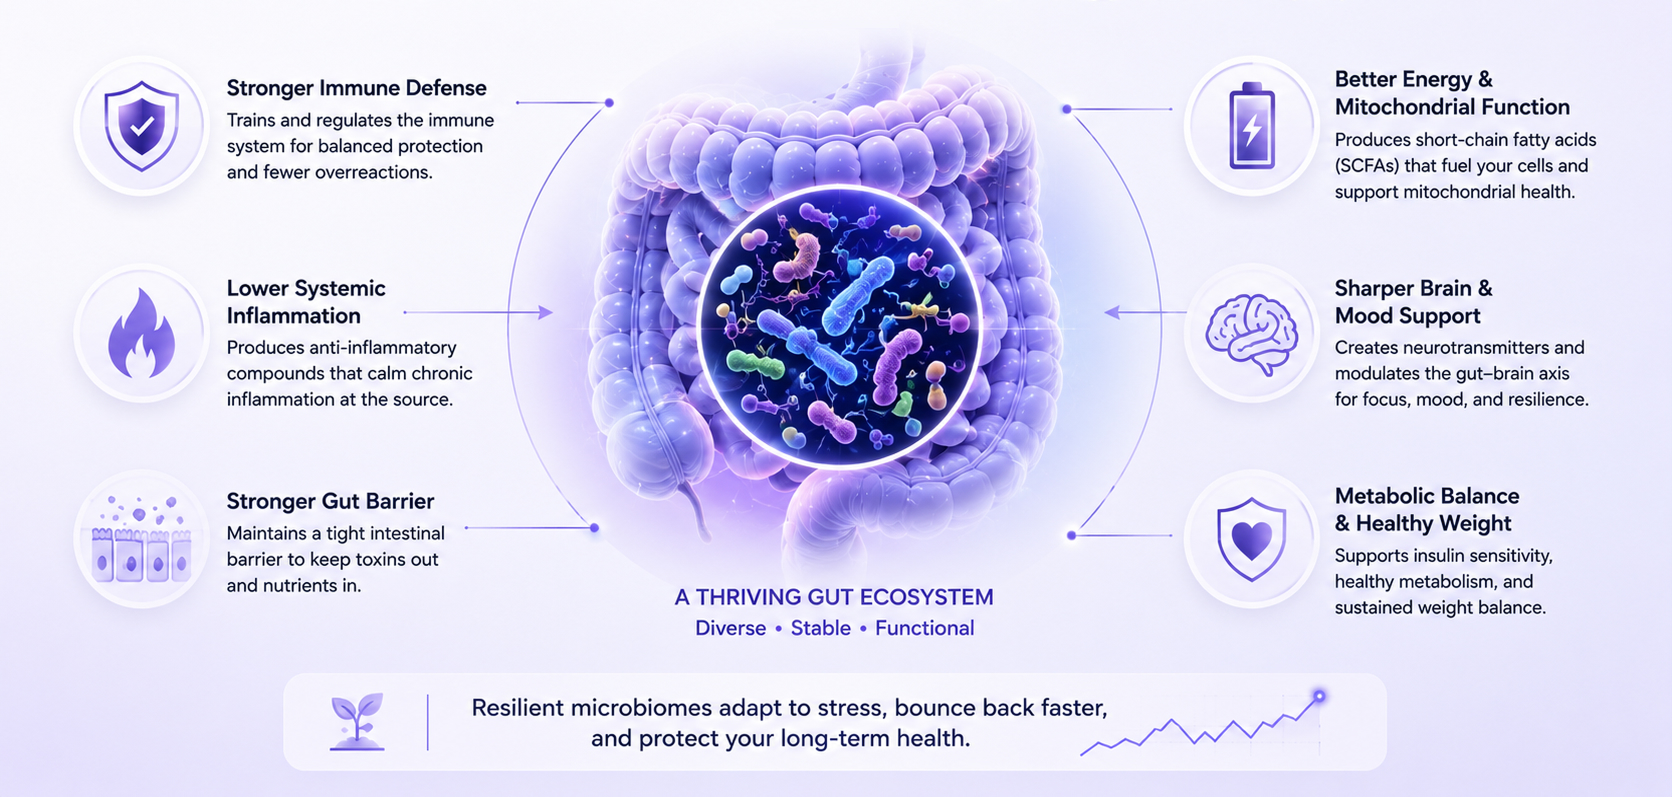
The athletes studied in the Irish cricket cohort—an elite group with high baseline fitness and structured nutritional support—still showed reductions in alpha diversity and shifts in taxonomic profiles following travel. Fitness and general health do not confer microbiome resilience. What does?
Pre-travel microbial diversity is the primary buffer variable. Higher baseline diversity correlates with faster compositional recovery after perturbation events. This is the ecological stability principle applied to the gut: diverse ecosystems absorb disruption more effectively than simplified ones because functional redundancy—multiple species capable of performing the same metabolic tasks—maintains critical outputs (butyrate production, barrier integrity) even as individual species populations fluctuate.
Butyrate-producing taxa, specifically Faecalibacterium prausnitzii, Akkermansia muciniphila, Christensenellaceae, and Ruminococcaceae, are the functional anchors. Their depletion is the earliest measurable signal of travel-induced dysbiosis, and their preservation is the primary objective of any pre- and peri-travel biological resilience strategy.
The Longevity Perspective
The Philadelphia–Naples–Palm Beach circuit is an asset—the ability to operate across three distinct environments is a function of success, not a problem to be solved. The clinical goal is not to eliminate travel but to prevent the cumulative biological cost of recurring unmanaged perturbation from expressing itself years earlier than it otherwise would.
What we are protecting is not gut comfort. We are protecting butyrate production, which sustains intestinal barrier integrity, which governs systemic inflammatory tone, which is upstream of mitochondrial efficiency, cognitive performance, and biological age acceleration. The microbiome is not a peripheral wellness variable—it is the regulator of the biological systems that determine how you age.
If you are making this transition more than four times annually across the Southwest Florida and Palm Beach corridor and have not formally assessed your baseline microbiome composition, inflammatory markers, and gut barrier function, you are managing a consequential biological asset without a dashboard. The diagnostic work is straightforward. The window to intervene early—before the cumulative deficit becomes clinically visible—is finite.
The three-phase clinical protocol for high-frequency travelers across the Philadelphia–Naples–Palm Beach circuit is available as a complete clinical reference document—including pre-departure, in-transit, and stabilization interventions with specific clinical rationale.
Dr. Banerjee is a board-certified gastroenterologist with over 15 years of clinical experience, peer-reviewed publications indexed in PubMed, and deep expertise in gut microbiome science. He advises high-achieving individuals and families on precision longevity and healthspan optimization across Pennsylvania, Florida, and Texas.
Selected References
1. Thaiss CA, Zeevi D, Levy M, et al. Transkingdom control of microbiota diurnal oscillations promotes metabolic homeostasis. Cell. 2014;159(3):514-529.
2. Matenchuk BA, Mandhane PJ, Kozyrskyj AL. Sleep, circadian rhythm, and gut microbiota. Sleep Medicine Reviews. 2020;53:101340.
3. Li Q, Wang B, Qiu HY, et al. Chronic jet lag exacerbates jejunal and colonic microenvironment in mice. Frontiers in Cellular and Infection Microbiology. 2021;11:648175.
4. Olson M, Withrow D, Koelbel M, et al. Sleep and circadian rhythm health on gastrointestinal microbiota. Sleep Medicine Reviews. 2026;86:102256.
5. Bautista J, et al. Bidirectional interactions between circadian rhythms and the gut microbiome. Applied Microbiology and Biotechnology. 2025;109(1):218.
6. DuPont HL. Microbiome alterations during and after international travel. Journal of Travel Medicine. 2025.
7. Worby CJ, Sridhar S, Turbett SE, et al. Gut microbiome perturbation and international travel. The Lancet Microbe. 2023;4(10):e790-e799.
8. Boolchandani M, et al. Impact of international travel and diarrhea on gut microbiome dynamics. Nature Communications. 2022;13(1):7485.
9. O’Donovan CM, et al. Altered gut microbiomes among Irish cricketers over periods of travel. Travel Medicine and Infectious Disease. 2020;35:101553.
10. Cheng M, et al. Microbiome resilience and health implications for people in half-year travel. Frontiers in Immunology. 2022;13:848994.

Should You Get a Gut Microbiome Test? A Gastroenterologist’s Evidence-Based Perspective
Last week, a patient arrived in my clinic with results from a direct-to-consumer gut microbiome test. The report labeled her as “deficient” in multiple bacterial species and recommended several probiotic supplements. It included polished graphics, percentile rankings, and a composite “dysbiosis score.”
The challenge was not the presentation—it was the interpretation. The test measured relative bacterial abundance, not microbial function. The reported “deficiencies” reflected comparisons to a reference population of uncertain clinical relevance, rather than actionable biological deficits. Without functional context, these results risked driving unnecessary interventions and expense.
This scenario is increasingly common. As gut microbiome testing becomes more accessible, patients and clinicians alike are confronted with reports that appear precise but often lack clinical clarity. Understanding what these tests measure, their limitations, and when they add real value is essential.
In this article, I will clarify how gut microbiome tests work, what they can and cannot tell us, and how to determine whether testing is appropriate for your health goals.
Executive Summary
- The gut microbiome plays a central role in metabolism, inflammation, immune regulation, and overall healthspan
- Gut microbiome testing analyzes stool samples using DNA sequencing to assess microbial composition and functional capacity
- The two primary testing methods—16S rRNA sequencing and shotgun metagenomic sequencing—offer different levels of insight and clinical utility
- Microbiome tests do not diagnose disease and represent a snapshot in time, not a fixed biological state
- When interpreted appropriately, microbiome testing can enhance precision care; when used in isolation, it can be misleading

The Core Question: What Are We Actually Measuring?
Modern microbiome tests use DNA sequencing to identify microorganisms in your stool. But not all sequencing methods are created equal, and understanding the difference is critical to interpreting what your results actually mean.
16S rRNA Gene Sequencing: The Industry Standard
This is what most consumer tests and many clinical labs use. It works by targeting a specific bacterial gene—the 16S ribosomal RNA gene—that serves as a genetic fingerprint for bacterial identification.
What it does well:
- Identifies bacteria at the genus level (like identifying "Bifidobacterium" but not which specific species)
- Provides a snapshot of overall microbial diversity
- Relatively affordable and fast
- Uses well-established reference databases
Critical limitations:
- Measures relative abundance, not absolute numbers. If you have less Bacteroides, it might mean you actually have fewer Bacteroides, or it could just mean other bacteria increased. The test can't tell the difference.
- Limited species/strain identification. This matters because Lactobacillus rhamnosus GG has clinical evidence, but "Lactobacillus genus" tells us almost nothing actionable.
- No functional information. It's like having a list of kitchen ingredients but no idea what meal you can make. Knowing bacteria are present doesn't tell you what they're producing.
My clinical perspective: 16S sequencing gives you a compositional overview—useful for assessing severe dysbiosis or tracking major shifts after intervention, but often insufficient for precision treatment planning.
Shotgun Metagenomic Sequencing: The Comprehensive Approach
This method sequences all the DNA in your stool sample—not just bacterial genes, but everything present.
What it offers:
- Species and strain-level identification
- Detection of bacteria, archaea, fungi, and viruses
- Functional profiling—analysis of metabolic pathways and gene capacity
- Insight into antimicrobial resistance genes
Why this matters for longevity: Functional data tells us whether your microbiome has the genetic machinery to produce butyrate, metabolize polyphenols, synthesize certain vitamins, or generate inflammatory compounds. This is clinically meaningful information that composition alone cannot provide.
The trade-offs:
- Higher cost
- More complex interpretation
- Requires sophisticated bioinformatics and clinical integration
- Still doesn't tell us what's actually being produced in real-time
When I order shotgun sequencing: For complex cases with treatment-resistant symptoms, metabolic dysfunction despite dietary optimization, or when I need to understand functional capacity before targeted interventions.
What Microbiome Testing Is Not
Let's clear up common confusion:
Traditional stool tests (culture, ova & parasite exams, PCR panels) are not microbiome tests. These look for specific pathogens—they're diagnostic tools for acute infections, not ecosystem profiling. They won't tell you about diversity, composition, or functional capacity.
Blood tests for "leaky gut" or food sensitivities are not microbiome tests. While gut barrier function and immune responses relate to the microbiome, these tests measure different phenomena and shouldn't be conflated with microbiome analysis.
The Technologies You'll Hear About Next
The field is evolving rapidly. Here's what's emerging from research into clinical practice:
Metatranscriptomics: Instead of DNA, this measures RNA. Think of it as the difference between having a recipe book and actually cooking the meal.
Metabolomics: Directly measures the chemical compounds produced by your microbiome—short-chain fatty acids, bile acids, tryptophan metabolites. This is the closest we get to understanding actual physiological impact, and in my view, represents the future of actionable testing.
Mycobiome and virome analysis: Specialized sequencing for fungal communities and bacteriophages. Emerging evidence suggests these play significant roles in health, but clinical applications are still being defined.
These technologies are mostly research-based today but will likely become standard within 5-10 years as costs decrease and interpretation frameworks mature.
My Clinical Framework
When patients ask about microbiome testing, I walk through these questions to maximize the value of their investment:
- What specific question are we trying to answer? "I want to optimize my gut health" is too vague. "I want to understand why I'm still bloated despite FODMAP elimination" is actionable and guides us toward the right test.
- Will the results guide personalized intervention? Testing shines when it reveals specific imbalances that direct targeted treatment—whether that's particular prebiotic fibers, antimicrobial protocols, or dietary modifications you wouldn't have tried otherwise.
- Are we measuring the right thing? Matching the test to your clinical picture maximizes insight. Functional analysis for metabolic concerns, compositional assessment for dysbiosis, targeted sequencing when specific organisms are suspected.
- How will we integrate results with your complete picture? Microbiome data becomes powerful when combined with your symptoms, dietary patterns, medication history, and inflammatory markers—this integration reveals patterns single data points miss.
- What's the intervention and reassessment plan? The greatest value comes from testing, implementing targeted changes, then retesting to confirm improvement—creating a feedback loop that refines your personalized protocol.
The Bottom Line
Microbiome testing can be a valuable clinical tool when:
- Ordered for specific indications, not general curiosity
- Interpreted by someone who understands both the technology and the clinical context
- Used to guide targeted interventions, not generate anxiety about bacterial "deficiencies"
- Followed by appropriate reassessment to measure intervention success.
The microbiome matters immensely for healthspan and longevity. But understanding what to measure, when to measure it, and how to act on results separates useful clinical data from expensive noise.
Dr. Banerjee is a board-certified gastroenterologist with over 15 years of clinical experience, peer-reviewed publications indexed in PubMed, and deep expertise in gut microbiome science. He advises high-achieving individuals and families on precision longevity and healthspan optimization. Expanded clinical analysis is available through the Private Longevity Briefing.
Selected Peer-reviewed evidence
- Chen S, Chen W, Wang X, Liu S. Mendelian randomization analyses support causal relationships between gut microbiome and longevity. J Transl Med. 2024;22(1):1032. Published 2024 Nov 16. doi:10.1186/s12967-024-05823-2
- Zhang G, Lu Y, Wang Z, et al. Causal relationship between gut microbiota and ageing: A multi-omics Mendelian randomization study. Arch Gerontol Geriatr. 2025;131:105765. doi:10.1016/j.archger.2025.105765
- Liu X, Zou L, Nie C, et al. Mendelian randomization analyses reveal causal relationships between the human microbiome and longevity. Sci Rep. 2023;13(1):5127. Published 2023 Mar 29. doi:10.1038/s41598-023-31115-8
- He D, Liu L, Zhang Z, et al. Association between gut microbiota and longevity: a genetic correlation and mendelian randomization study. BMC Microbiol. 2022;22(1):302. Published 2022 Dec 13. doi:10.1186/s12866-022-02703-x
- Porcari S, Mullish BH, Asnicar F, et al. International consensus statement on microbiome testing in clinical practice. Lancet Gastroenterol Hepatol. 2025;10(2):154-167. doi:10.1016/S2468-1253(24)00311-X